How Smaller Elderly Care Settings Improve Safety, Guidance, and Assistance
Business Name: BeeHive Homes of Volcano Cliffs
Address: 6230 Montaño Rd NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Volcano Cliffs
At BeeHive Homes of Volcano Cliffs, New Mexico, we offer the finest assisted living experience available in a cozy, comfortable homelike setting. Each of our residents has their own spacious room with an ADA approved bathroom and shower. We prepare and serve delicious home-cooked meals three times a day every day. We maintain a small, friendly elderly care community. We provide regular activities that our residents find fun and contribute to their health and well-being. Our staff is attentive and caring and provides assistance with daily activities to our senior living residents in a loving and respectful manner. We would like to invite you to tour and experience our assisted living home and feel the difference.
6230 Montaño Rd NW, Albuquerque, NM 87120
Business Hours
Most households start checking out senior care after a scare: a fall in your home, a medication mix‑up, a wandering event, or a steady decrease that suddenly becomes impossible to disregard. In those minutes, the world of assisted living and elderly care can seem like an alphabet soup of options and sales language. Buried in the information is one aspect that silently forms practically whatever about a resident's life: the size of the care setting.
Having worked with older grownups in both big neighborhoods and small residential homes, I have actually seen the distinction that scale makes. Bigger is not automatically worse, and smaller is not instantly much better. But when the concern is safety, close supervision, and truly personalized support, attentively run smaller settings have some structural advantages that are hard to replicate in a big structure with a hundred residents.
This does not suggest everyone ought to hurry toward the smallest home they can discover. It implies households should understand how size affects care, what trade‑offs are involved, and how to tell a well run small environment from one that merely calls itself "relaxing".
What "small" truly suggests in elderly care
People use the term "small" to describe whatever from a 20‑apartment assisted living wing to a four‑bed residential care home. To comprehend the influence on security and guidance, it assists to draw some rough lines.
In numerous areas, senior care settings fall under three broad groups:
- Large neighborhoods: typically 60 to 200 homeowners, frequently with multiple floorings, dining spaces, and activity spaces.
- Mid sized facilities: approximately 20 to 60 residents, typically a single structure or wing, often part of a larger campus.
- Small residential settings: generally 3 to 16 locals, frequently accredited as adult household homes, board‑and‑care, residential care homes, or comparable names depending on the state or country.
The labels vary by jurisdiction, but the lived experience in a 10‑resident home is very various from that in a 120‑resident facility.
In a big assisted living neighborhood, the advantages typically center on facilities: restaurant‑style dining, regular activities, on‑site treatment, transportation, and a sense of a "village" under one roofing. The trade‑off is that staff needs to cover a great deal of ground. A caregiver may be responsible for 12 to 18 residents during a shift, in some cases more, typically spread across a long corridor or multiple wings.
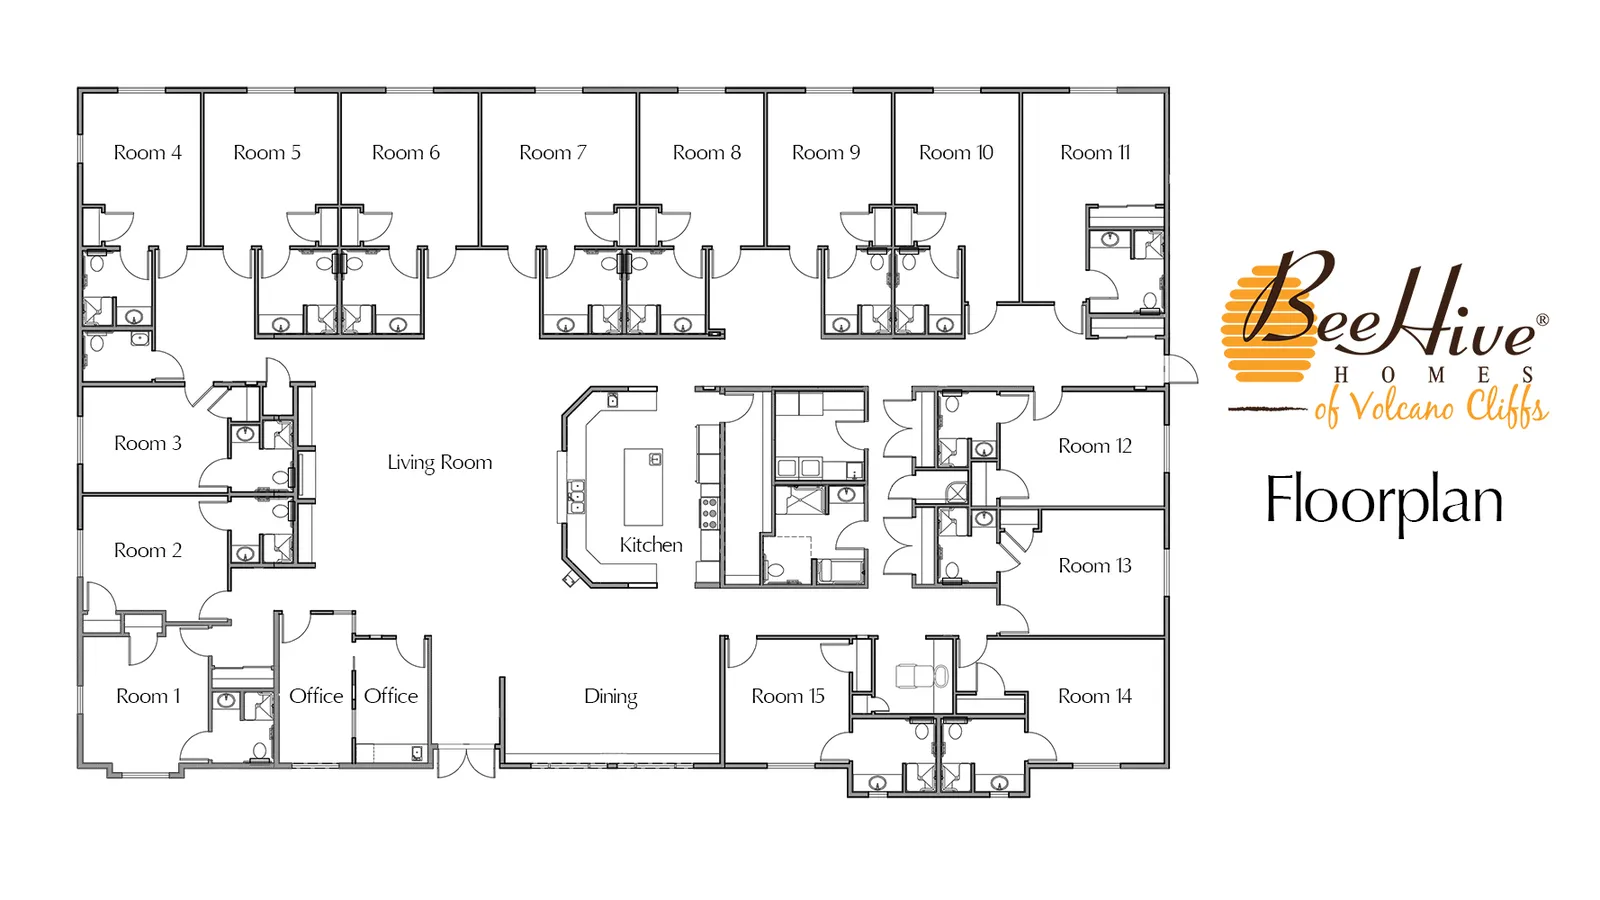
In a genuinely small elderly care home, there might be 1 or 2 caregivers for 6 to 10 citizens, all within line of sight or simply a brief corridor away. There is generally one cooking area, one primary living area, and bedrooms nestled closely around them. What you quit in glossy amenities, you gain in distance. That proximity is what equates into safety and supervision.
Why physical scale shapes safety
When we discuss "security" in senior care, we are really talking about particular dangers: falls, wandering and exit‑seeking, medication errors, choking and goal, postponed action in emergency situations, and undetected modifications in health status. Size affects each of these, frequently in subtle ways.
In a smaller setting, staff can actually hear more. A chair scraping on tile, a closet door opening, a resident muttering in the hallway at 3 a.m. These small noises frequently precede an occurrence. In a large structure with long corridors, heavy fire doors, and mechanical noise, those early cues are simple to miss.
One afternoon in a 9‑bed home, a caregiver I worked with paused mid‑conversation and stated, "That is not her normal cough." She walked down the hall, checked on a resident, and discovered that she had actually started aspirating on a sip of water. Quick intervention, urgent call to the physician, healthcare facility visit, and the resident recuperated. Would that have been caught as quickly in a dining room with 70 people discussing clattering meals? Possibly, however less likely.
Smaller environments likewise decrease the distance in between danger and action. If a resident stands up unsteadily, a caretaker three actions away can provide an arm. In a huge center, a resident may walk an unexpected distance before anyone notifications, especially if staffing ratios are stretched at particular times of day.
None of this means large communities can not be safe. Lots of are, and they typically have more video cameras, nurse protection, and safety innovation. But technology hardly ever compensates for the basic truth that in a smaller area, it is harder for a problem to stay concealed for long.
Staff visibility and supervision
Supervision is not practically seeing individuals; it is about knowing them all right to notice change. Smaller elderly care homes tend to create that familiarity by design.
In a 6 to 12 resident home, every caregiver usually knows:
- Each resident's typical strolling speed and posture.
- How they like their coffee or tea.
- Which jokes land and which do not.
- What "typical" confusion looks like for that individual and what feels off.
That collected understanding ends up being a casual early‑warning system. A seasoned caregiver in a small setting will typically say things like, "She is quieter at breakfast today; something is brewing" or "He usually sleeps after lunch, but he has been pacing for an hour." That sort of pattern acknowledgment is much more difficult when someone is managing 15 locals throughout two hallways.
Larger assisted living neighborhoods attempt to develop supervision through systems: regular rounding, electronic care notes, incident reports, set up assessments. Those are very important, but they can develop a rhythm where staff react to tasks rather than to individuals. In a small home, tasks are still there, however they are woven into normal household life. Personnel see residents from multiple angles in a single day: at the kitchen area table, in the hallway, in the garden, throughout a television show. Guidance is constructed into every interaction.
Families often see this difference during respite care. A loved one might remain for two weeks in a 100‑resident community, then two weeks in an 8‑resident home. In the bigger neighborhood, the household might get a packet of notes, a care summary, and scheduled updates. In the smaller home, they typically hear, "She has begun humming again after lunch; she appears more relaxed" or "He is consuming much better if we sit with him and serve smaller portions first." Both methods have value, but for delicate adults with dementia, the granular observations frequently avoid bigger problems.
Medication management and medical oversight
Medication mistakes are among the most typical security risks in any senior care environment. Missing out on a dose of blood pressure medication might not cause an instant crisis. Doubling insulin or mishandling blood slimmers can.
In bigger centers, medication management typically depends on medication carts, set up "med passes," bar‑code scanning, and different medication technicians. That structure can be really safe when staffing is stable and workflow is well arranged. The risk begins busy shifts: a smoke alarm, a fall, three residents requesting assistance simultaneously, and a med tech fast moving through a long list.
In smaller settings, there is seldom a med cart rolling down halls. Medications are usually kept in a locked cabinet or space, and the exact same caregivers who help with bathing and meals likewise manage regular medications, within their training and the regulations of their area. The resident list is much shorter, the timing more versatile. Staff might provide high blood pressure pills over breakfast, eye drops in the restroom a few minutes later, and prescription antibiotics throughout afternoon tea.
The safety advantage here comes from two aspects. First, less residents mean less complex schedules to juggle simultaneously. Second, caretakers typically discover patterns quickly: "She is swiping her tablets in the afternoon; we ought to try considering that one crushed with applesauce" or "He looks off whenever we increase that dose." That feedback loop between observation and medical change tends to be tighter in a smaller environment, especially when a nurse or doctor is available and engaged with the home.
That said, tiny homes can fall short if they do not have strong scientific oversight. Families must ask how the home coordinates with physicians, who evaluates medications regularly, and how staff are trained. A small house without great systems can be more dangerous than a big neighborhood with robust medical protocols.
Fall risk and the design of day-to-day life
Falls rarely take place out of no place. They creep up through subtle shifts: a somewhat longer range to the restroom, a brand-new thick carpet in the hallway, a chair positioned a little too far from the table. In a large facility, upkeep and style choices are produced lots of individuals at the same time. That can work, but it undoubtedly suggests compromise.
In a small elderly care home, the physical environment is more like a basic home: fewer stairs, much shorter ranges, and typically one primary area where people collect. Personnel relocation through the exact same spaces continuously. If a rug starts to curl at the corner, someone usually trips gently or notices it within a day or 2, not weeks later on during a main inspection.
The scale likewise allows for practical personalization. If a resident with Parkinson's freezes in narrow areas, corridor furniture can be reorganized rapidly. If somebody with dementia confuses the restroom door, personnel can include a colored indication or memory cue simply for that person. These small environmental tweaks directly reduce fall threat and wandering without feeling institutional.
I keep in mind one resident, a previous carpenter, who kept trying to "repair" things in a big structure. In the smaller home he relocated to later on, staff gave him a safe tool kit with blunt tools senior care and small tasks: tightening up cabinet knobs, inspecting chair legs. His restless walking became purposeful movement, and his fall occurrences dropped over the next months. That sort of versatile reaction is much easier to attempt when you are handling a single living room, not a five‑floor complex.
Emotional security and the rhythm of the day
Physical security is only half the story. Emotional safety matters just as much, specifically for older adults coping with memory loss, stress and anxiety, or depression.
Large neighborhoods usually work on schedules adjusted for functional performance. Breakfast from 7 to 9, activities at 10, lunch at 12, showers on appointed days, medication passes at set times. Numerous homeowners value the structure and variety, but particular individuals can feel swept along by a timetable that does not match their natural rhythm.
In a small residential senior care home, the speed is closer to domestic life. If someone chooses coffee at 6 a.m. And breakfast at 9, it is much easier to accommodate. If another resident sleeps badly and wants to sit quietly with a caretaker at 3 a.m. Enjoying old films, there is room for that without interfering with dozens of others.
This flexibility has a direct impact on agitation, specifically in locals with dementia. When individuals are not constantly being hurried, lined up, or asked to adapt to group schedules, they tend to be calmer and less resistant. Less agitation ways less incidents that escalate to physical restraint, sedating medications, or emergency transfers.
I have seen households shocked by how a parent's "behavior problems" soften in a small assisted living or board‑and‑care home. A lady who hit staff in a big memory care unit stopped doing so when she might consume in a small group at a home‑style table and invest afternoons folding towels in the cooking area. The habits had been an interaction of overwhelm, not an unchangeable personality trait.
The role of smaller settings in respite care
Respite care is often the very first genuine test of any elderly care plan. A short stay offers everybody an opportunity to see how a setting manages unknown routines, medical conditions, and emotional needs.
In a large assisted living or memory care community, respite stays can be highly structured: formal admission assessments, printed care plans, a set room for a minimal time, often a minimum stay requirement. This works well for seniors who adapt quickly to brand-new environments and enjoy activity calendars filled with options.
Smaller homes tend to incorporate respite locals straight into every day life. There might be an extra bedroom that becomes "Grandpa's space," with the exact same caregivers and regimens as permanent citizens. On the first day, personnel might sit down with the household at the kitchen area table, review medications and preferences, and view how the individual moves, eats, and interacts.
For caregivers at home who are currently stretched thin, sending out a loved one to a small residential home for respite can feel closer to handing them to an extended household. That sense of continuity impacts how willingly older adults accept the break. A male who declined respite in a big structure with hectic passages in some cases agrees to "remain for a few days in that home with the garden and friendly dog."
Respite is likewise where supervision quality ends up being noticeable rapidly. Households returning after a week can detect information: Is the laundry done and identified effectively? Does their loved one keep in mind personnel names and feel at ease? Does the personnel recount particular occasions and preferences, or only refer to generic "She did great"?
Family participation and transparency
One of the quiet strengths of smaller elderly care homes is the transparency that comes with minimal area. Families see more of what occurs, excellent and bad.
When you stroll into a large senior care facility, you generally pass through a lobby, maybe a receptionist, then down hallways to a resident's room. You see a slice of life: a couple of staff, some citizens in common spaces, decoration, published menus and calendars. Much happens behind doors and on other floors.
In a smaller home, you frequently step straight into the primary living area. The cooking area smells are right there. You can hear how staff speak to homeowners, notification whether call lights are going unanswered, and see who is actually on shift. If something feels off, it is hard for the environment to hide it.
This visibility can reinforce partnership. Families are more likely to have casual chats with caregivers, share observations, and adjust care together. That ongoing discussion typically captures issues early: skin changes, mood shifts, household dynamics, financial questions. It likewise constructs trust, which is vital when tough decisions occur about hospitalizations, hospice, or transitions.
Trade offs and limitations of smaller settings
Small does not suggest ideal. Every model of senior care has trade‑offs, and it is very important to take a look at them honestly.
One obstacle is staffing depth. A large assisted living community with 80 homeowners may have a nurse on site every day, plus multiple caregivers, med techs, and backup personnel. If somebody calls in ill, there is usually a swimming pool to draw from. In a 6‑resident home, losing even one caregiver to disease can strain the team if there is not a strong backup plan.
Another problem is access to on‑site services. Larger structures might provide on‑site physical treatment, going to professionals, drug store shipment several times a day, and transportation vans. A small residential care home may rely more on outside companies coming in or families organizing visits. For extremely clinically complex residents, that additional coordination can be a burden.
Social range is likewise different. Some outgoing seniors prosper in a large neighborhood with lots of potential pals and numerous activities every day. They take pleasure in the feeling of "heading out" to performances, lectures, and workout classes without leaving the structure. In a small home, the social circle makes love. For some, that seems like household. For others, it can feel limiting.
Regulation and oversight can differ as well. In lots of regions, small centers are certified under various classifications with different evaluation frequencies. Some are outstanding and firmly run; others cut corners. Families can not assume that "home‑like" instantly indicates "high quality."

The secret is to match the setting to the person's needs and personality, and after that evaluate the real operation of the home, not just its size.
A brief contrast: where small settings typically excel
Used thoroughly, a succinct comparison can clarify where small elderly care homes tend to have an edge. For numerous residents with safety and guidance requirements, smaller environments normally provide:
- Shorter response times when someone requires assistance or an alarm sounds.
- Closer observation and earlier detection of modifications in health or behavior.
- More versatile day-to-day routines that decrease agitation and resistance.
- Stronger staff‑resident relationships, resulting in tailored support.
- Easier family interaction and greater openness day to day.
These are propensities, not guarantees. Some big communities work hard to match or even go beyond these qualities. Still, the structural benefits of distance and familiarity are tough to ignore.
How to assess a small elderly care home
For families thinking about a relocate to a smaller setting, the key is not just "Is it small?" however "Is it well run, safe, and lined up with our needs?" It assists to ground the search in a short mental list throughout visits.
Here is one simple way to focus your attention while touring or setting up respite care:
- Watch how staff speak to locals: tone, persistence, eye contact, and whether they utilize names.
- Notice smells and sounds: strong smells, continuous alarms, or raised voices can signal problems.
- Ask particular concerns about staffing ratios on nights and weekends, not just weekdays.
- Look for in-depth knowledge: can staff describe each resident's choices and health issues?
- Clarify how emergency situations, medical facility transfers, and communication with families are handled.
You are not just purchasing a space; you are signing up with a small ecosystem. The quality of that environment will shape your loved one's security and sense of home more than any brochure.
Where smaller settings suit the bigger senior care landscape
Elderly care is rarely a straight line. Many older adults move between levels and types of care over time: independent living, assisted living, memory care, health center stays, competent nursing, and hospice. Small residential homes and intimate assisted living settings fill an essential niche because landscape.
For those who are too frail or cognitively impaired to live alone, however who do not need the strength of a nursing home, a small setting can supply the best level of structure and supervision without sacrificing dignity and uniqueness. For family caregivers nearing burnout, a short respite in a small home can prevent crisis and extend the possibility of continued care at home.
The pattern in lots of regions has been a gradual shift towards these "home within a home" designs. Some big campuses now design their memory care or high‑acuity assisted living as clusters of small families under one bigger umbrella. Each household may host 10 to 14 citizens, with its own kitchen and care team. That hybrid technique tries to blend the intimacy of small homes with the resources of a large organization.
At its finest, elderly care is not about structures at all. It has to do with relationships, routines, and actions to vulnerability. Smaller settings, when thoughtfully staffed and well managed, typically make those human components simpler to provide. They produce environments where staff can truly know residents, where households can stay closely included, and where safety is the outcome of consistent, peaceful listening rather than occasional crisis response.
For families standing at the crossroads of senior care choices, taking note of size is not a minor detail. It is a useful method to anticipate how well a setting will secure your loved one from preventable harm, how carefully they will be monitored, and how personally they will be supported in the daily business of living the later chapters of their life.
BeeHive Homes of Volcano Cliffs provides assisted living care
BeeHive Homes of Volcano Cliffs provides respite care services
BeeHive Homes of Volcano Cliffs supports assistance with bathing and grooming
BeeHive Homes of Volcano Cliffs offers private bedrooms with private bathrooms
BeeHive Homes of Volcano Cliffs provides medication monitoring and documentation
BeeHive Homes of Volcano Cliffs serves dietitian-approved meals
BeeHive Homes of Volcano Cliffs provides housekeeping services
BeeHive Homes of Volcano Cliffs provides laundry services
BeeHive Homes of Volcano Cliffs offers community dining and social engagement activities
BeeHive Homes of Volcano Cliffs features life enrichment activities
BeeHive Homes of Volcano Cliffs supports personal care assistance during meals and daily routines
BeeHive Homes of Volcano Cliffs promotes frequent physical and mental exercise opportunities
BeeHive Homes of Volcano Cliffs provides a home-like residential environment
BeeHive Homes of Volcano Cliffs creates customized care plans as residents’ needs change
BeeHive Homes of Volcano Cliffs assesses individual resident care needs
BeeHive Homes of Volcano Cliffs accepts private pay and long-term care insurance
BeeHive Homes of Volcano Cliffs assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Volcano Cliffs encourages meaningful resident-to-staff relationships
BeeHive Homes of Volcano Cliffs delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Volcano Cliffs has a phone number of (505) 302-1919
BeeHive Homes of Volcano Cliffs has an address of 6230 Montaño Rd NW, Albuquerque, NM 87120
BeeHive Homes of Volcano Cliffs has a website https://beehivehomes.com/locations/volcano-cliffs/
BeeHive Homes of Volcano Cliffs has Google Maps listing https://maps.app.goo.gl/vC78eXZrUYuJ298v9
BeeHive Homes of Volcano Cliffs has Instagram page https://www.instagram.com/beehivealbuquerquewest
BeeHive Homes of Volcano Cliffs has an TikTok page https://www.tiktok.com/@beehivehomesalbuq
BeeHive Homes of Volcano Cliffs won Top Assisted Living Homes 2026
BeeHive Homes of Volcano Cliffs earned Best Customer Service Award 2025
BeeHive Homes of Volcano Cliffs placed 1st for Senior Living Communities 2026
People Also Ask about BeeHive Homes of Volcano Cliffs
What is BeeHive Homes of Volcano Cliffs Living monthly room rate?
Our base rate is $7,100 per month. We do an assessment of each resident's needs upon move-in, so each resident's rate may be slightly higher. However, there are no add-ons or hidden fees. We also charge a one-time community fee of $2,000 at move-in
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living. Some assisted living facilities are Medicaid providers, but we are not. We do accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock
What can you tell me about the food at Bee Hive?
You have to smell it and taste it to believe it! We use dietitian-approved meals with alternates for flexibility, and we can accommodate needs for different texture and therapeutic diets. We have found that most physicians are happy to relax diet restrictions without any negative effect on our residents
Do we allow pets?
We do allow small pets as long as the resident is able to care for them. State regulations also require that we have evidence of current immunizations for any required shots
Where is BeeHive Homes of Volcano Cliffs located?
BeeHive Homes of Volcano Cliffs is conveniently located at 6230 Montaño Rd NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday through Sunday 10:00am to 7:00pm
How can I contact BeeHive Homes of Volcano Cliffs?
You can contact BeeHive Homes of Volcano Cliffs by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/volcano-cliffs/ or connect on social media via Instagram Facebook or TikTok
K Style Kitchen provides a convenient local restaurant where families supporting loved ones through Assisted living memory care senior care elderly care and respite care can enjoy an outing together.